

Blog
Deca vs NPP: Which Nandrolone Ester Fits Your Cycle?

Deca and NPP are the same hormone — nandrolone — with a different ester attached. That single difference decides almost everything that matters in practice: how fast blood levels rise, how often you inject, how long a cycle needs to run, and how long you must wait before post-cycle therapy (PCT) can work. The short answer: NPP (nandrolone phenylpropionate) gets in and out faster, so it suits shorter cycles and anyone who wants a quicker exit; Deca (nandrolone decanoate) releases slowly and steadily, so it suits longer cycles and fewer injections. Neither ester is stronger in any absolute sense — the hormone doing the work is identical.
This guide compares the two esters on pharmacology, cycle planning, side effects and PCT timing, using published clinical and pharmacokinetic studies where they exist and marking clearly where the numbers come from community practice instead. Nandrolone is a controlled substance in Canada, listed in Schedule IV of the Controlled Drugs and Substances Act, and nothing here is medical advice. If you are considering use, talk to a doctor first and get bloodwork. The store’s Deca-Durabolin 300 mg/mL and NPP 100 mg/mL pages list the two products this comparison is about.
Same hormone, different ester
An ester is a fatty-acid chain attached to the steroid molecule so it dissolves in oil and releases slowly from the injection depot. Enzymes in the blood then cleave the ester off, freeing the same nandrolone molecule either way. A short ester chain (phenylpropionate) is cleaved quickly; a long one (decanoate) is cleaved slowly. That is the whole mechanism, and it explains every practical difference in the table below.
The cleanest direct evidence comes from Minto and colleagues (1997), who gave 23 healthy men a single 100 mg intramuscular injection of either ester and tracked blood levels for 32 days. The phenylpropionate ester produced higher and earlier peaks than the decanoate ester, while decanoate produced the most sustained suppression of the men’s own testosterone — exactly the trade-off this article is about: faster and higher with NPP, slower and longer with Deca.
Deca vs NPP: the head-to-head table
| Feature | NPP (nandrolone phenylpropionate) | Deca (nandrolone decanoate) |
|---|---|---|
| Active hormone | Nandrolone | Nandrolone |
| Ester length | Short (phenylpropionate) | Long (decanoate) |
| Time to peak after a 100 mg injection | 1–2 days | 3–6 days |
| Release pattern | Faster rise, faster fall | Slower rise, sustained release over weeks |
| Injection frequency in community practice | Every other day | Once or twice per week |
| Typical cycle length discussed | 8–10 weeks | 12–16 weeks |
| Clearance and PCT wait | Shorter — roughly 1–2 weeks after the last injection | Longer — roughly 3–4 weeks after the last injection |
| Best for | Shorter cycles, faster feedback, quicker exit | Longer cycles, fewer injections, steadier levels |
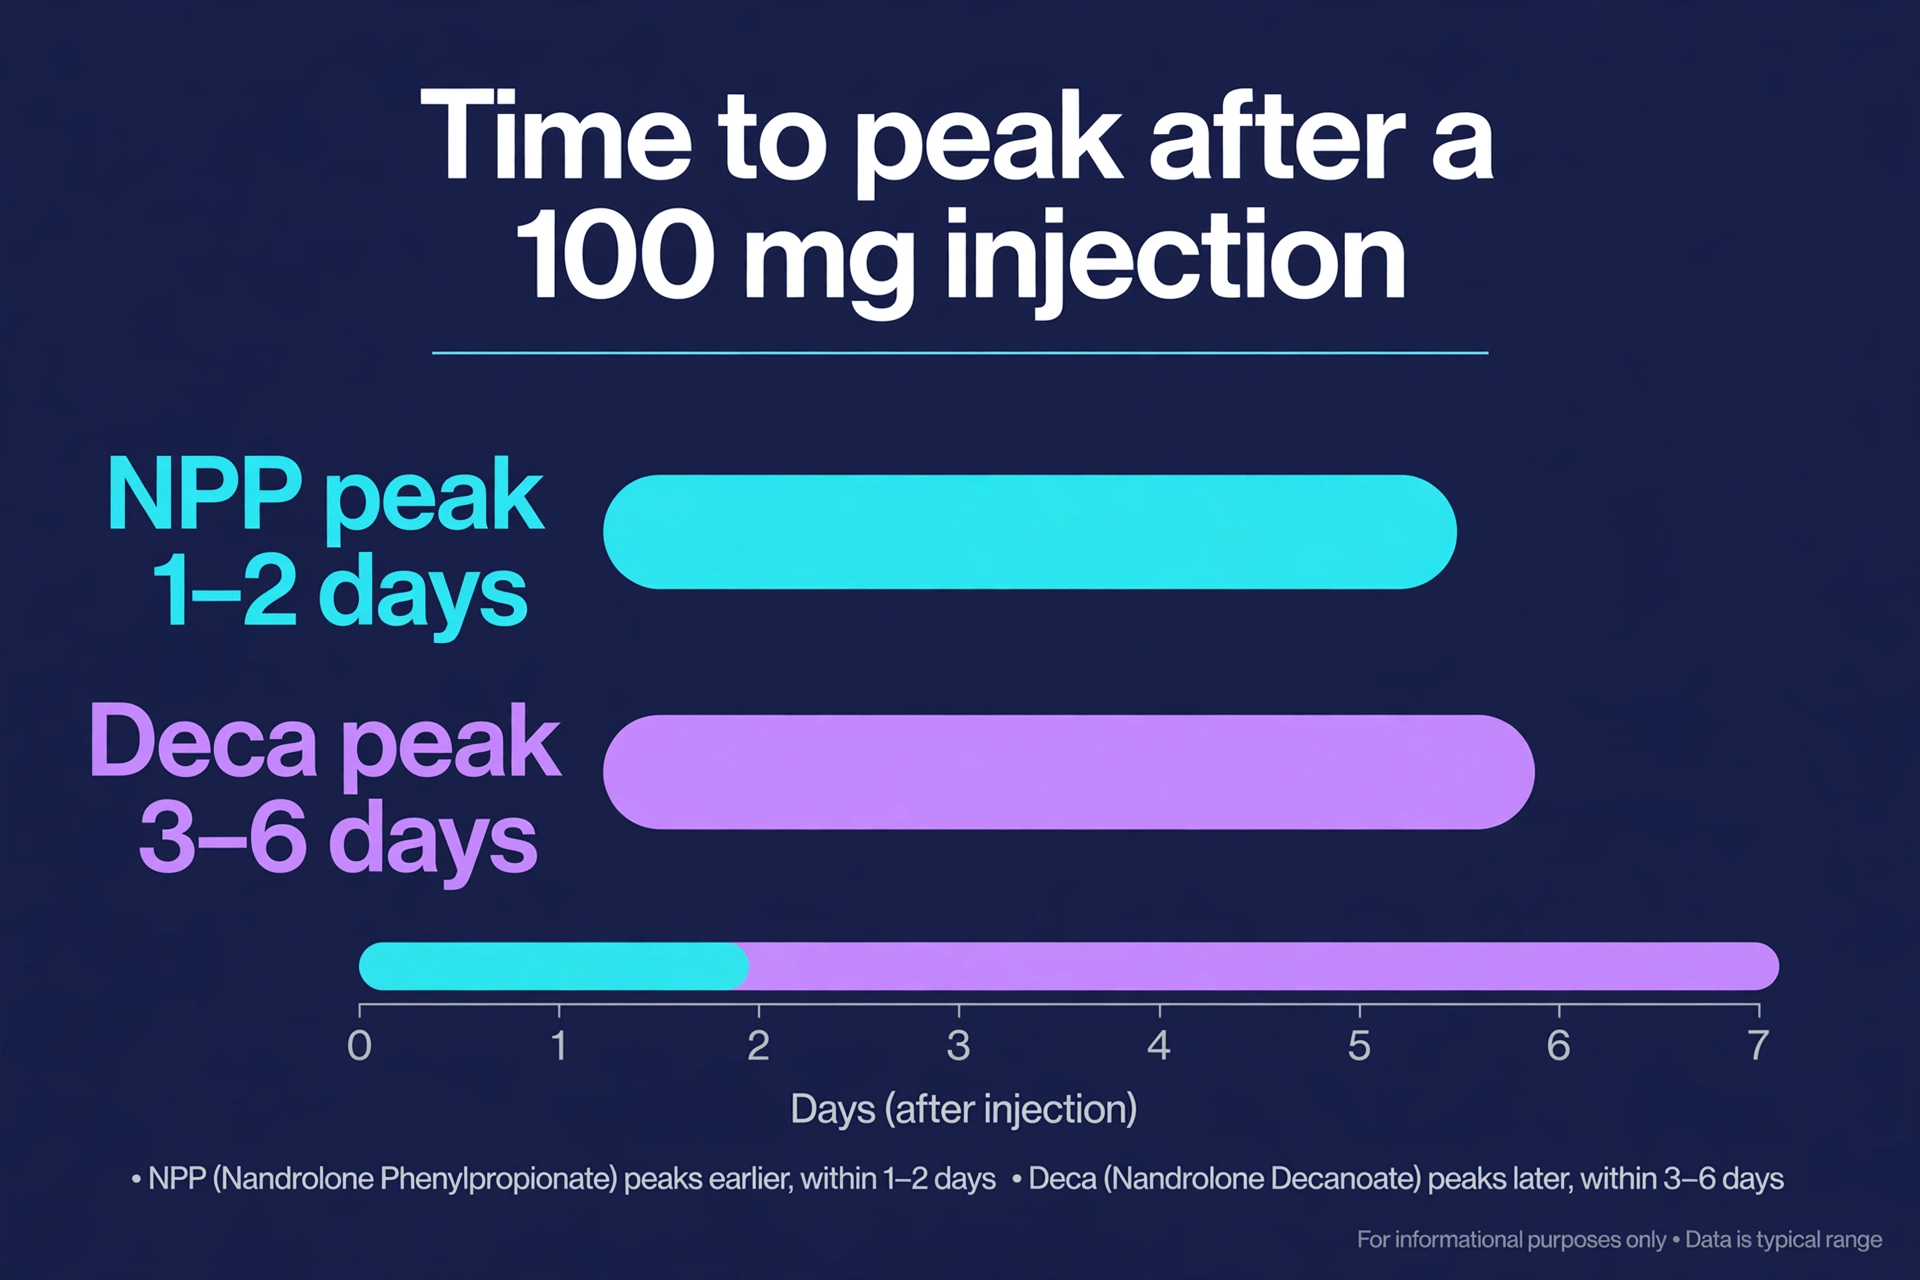
Peak-timing ranges are typical values for a 100 mg intramuscular dose; individual values vary with injection volume, site and carrier oil.
What the clinical evidence actually shows
There are no head-to-head trials of Deca versus NPP for muscle building. In Macdonald and colleagues’ 2007 randomized dose-finding study, 54 patients with stage 5 chronic kidney disease received 50, 100 or 200 mg of nandrolone decanoate per week for 24 weeks: appendicular lean mass rose +0.3 kg in controls, +0.8 kg, +1.5 kg and +2.1 kg respectively (p < 0.001). Doubling the dose from 100 to 200 mg added only 0.6 kg, while the highest female dose (100 mg per week) was intolerable because of virilizing effects.
| Group (Macdonald 2007, 24 weeks) | Weekly nandrolone decanoate dose (men) | Change in appendicular lean mass |
|---|---|---|
| Control | None | +0.3 kg |
| Low dose | 50 mg | +0.8 kg |
| Medium dose | 100 mg | +1.5 kg |
| High dose | 200 mg | +2.1 kg |
Appendicular lean mass change over 24 weeks, Macdonald et al. 2007.
A second trial points the same way. Johansen and colleagues (1999) randomized 29 dialysis patients to 100 mg of nandrolone decanoate weekly or placebo for 6 months: the nandrolone group gained 4.5 kg of lean body mass versus 1.9 kg on placebo. These were clinical patients, not athletes, at doses far below community cycle totals — which is why they are useful: they show the hormone works at modest doses, and say nothing that justifies very high doses.
One more fact matters for planning: in an early decanoate study, serum nandrolone remained elevated for 15–20 days after a single 50 mg decanoate injection. That long tail is Deca’s defining feature and its main drawback: weeks after your last injection, enough hormone can remain to keep your own testosterone suppressed. NPP’s tail is far shorter, so its PCT wait is days to a couple of weeks rather than a month.

Injection frequency and cycle planning
Because NPP clears quickly, community protocols inject it every other day to keep blood levels stable; skipping days produces peaks and troughs that tend to bring more side effects. That is three or four injections a week, each with its own small risk of site pain or infection. Deca, by contrast, is typically injected once or twice a week, which most users find far easier to sustain over a 12–16 week cycle.
Cycle length follows from the ester. A Deca cycle shorter than about 12 weeks barely gives the slow ester time to reach steady levels before it ends, which is why Deca cycles are usually discussed at 12–16 weeks. NPP reaches effective levels within days, so 8–10 week cycles are common in community reports. Our first testosterone cycle guide explains the same ester logic for testosterone. The injectable steroids category is where both nandrolone products sit alongside the other injectables.
Side effects: shared by both, different in timing
Because the hormone is the same, the side-effect profile is shared — what differs is onset and duration. Nandrolone suppresses your own testosterone production, and Minto’s study showed decanoate suppressed it for longest. Expect testicular shrinkage during use, reduced sperm count, and a recovery period afterwards that is longer after Deca than after NPP. Nandrolone converts to estrogen at a lower rate than testosterone, but estrogen-related effects (water retention, nipple sensitivity) still occur, and its progestogenic activity is why some users report prolactin-related symptoms such as lactation or sexual dysfunction; our estrogen management guide covers the ancillaries involved. Other shared risks include acne, hair shedding in those genetically prone to it, unfavourable lipid changes, raised haematocrit and blood pressure, and mood changes.
Two differences deserve emphasis. First, “Deca dick” — erectile difficulty on nandrolone — is widely reported and usually attributed to suppressed testosterone, raised prolactin activity and low estrogen from over-aggressive ancillary use; it is one reason nandrolone is almost always discussed alongside a testosterone base rather than alone. Second, detection time: nandrolone metabolites are detectable in urine for many months after use, and Deca’s long tail makes its detection window the longer of the two.
PCT timing: where the ester choice really bites
Starting PCT while the ester is still releasing hormone is wasted effort: your natural production stays suppressed until blood levels fall far enough. That is why the waiting period differs so much — roughly 1–2 weeks after the last NPP injection, versus roughly 3–4 weeks after the last Deca injection in community protocols. Our timing guide, when to start PCT after each ester, gives the full ester-by-ester chart, and the head-to-head Nolvadex vs Clomid comparison explains which PCT drug fits which situation. If you choose Deca, plan for a longer total commitment: a 14-week cycle plus a 4-week wait plus 4 weeks of PCT is 22 weeks before recovery is even assessed.
Which should you choose?
Choose NPP if you want a shorter cycle, faster feedback on how you respond, and a quicker exit if side effects appear — and you accept injections every other day. Choose Deca if you prefer once- or twice-weekly injections, are planning a longer cycle anyway, and do not mind waiting a month before PCT. If you are new to nandrolone, the faster feedback of NPP is the safer learning experience: a bad reaction costs days, not weeks.
One caution applies to both: do not run nandrolone without a testosterone base unless you have medical supervision. Nandrolone alone suppresses your testosterone while replacing only part of its function, which is how low-testosterone symptoms appear mid-cycle despite “being on” a steroid.
Harm-reduction checklist
Whatever ester you choose, the same basics apply. Get baseline bloodwork before starting (testosterone, estradiol, prolactin, complete blood count including haematocrit, liver enzymes, kidney function and lipids) and repeat the key markers after the cycle and after PCT. Use sterile technique every time: fresh needle and syringe, alcohol-wiped vial top and skin, rotated sites, never shared equipment. Watch for warning signs that need a doctor promptly: fever or spreading redness at an injection site, chest pain, breathlessness, leg swelling, severe headache, or a breast lump.
Frequently asked questions
Is Deca stronger than NPP?
No — milligram for milligram of nandrolone, they are the same hormone. Deca only appears “stronger” in long cycles because its slow release keeps levels up for longer, and NPP only appears “faster” because it peaks sooner.
Can I switch from Deca to NPP mid-cycle?
Possible in principle, since the hormone is identical — but Deca already in your system keeps releasing for weeks after you stop injecting it, so most protocols advise picking one ester per cycle and changing only between cycles, once levels have cleared.
How long after Deca or NPP can I start PCT?
Community protocols typically wait roughly 1–2 weeks after the last NPP injection and roughly 3–4 weeks after the last Deca injection, then run a SERM-based PCT and confirm recovery with bloodwork.
Does NPP cause fewer side effects than Deca?
Not fewer in kind — the side effects are the same — but with a shorter-acting ester they usually fade sooner after stopping. The trade-off is more frequent injections.
References
- Minto CF, Howe C, Wishart S, Conway AJ, Handelsman DJ. Pharmacokinetics and pharmacodynamics of nandrolone esters in oil vehicle: effects of ester, injection site and injection volume. Journal of Pharmacology and Experimental Therapeutics. 1997;281(1):93–102.
- Macdonald JH, Marcora SM, Jibani MM, Kumwenda MJ, Ahmed W, Lemmey AB. Nandrolone decanoate as anabolic therapy in chronic kidney disease: a randomized phase II dose-finding study. Nephron Clinical Practice. 2007;106(3):c125–c135. PMID: 17522475.
- Johansen KL, Mulligan K, Schambelan M. Anabolic effects of nandrolone decanoate in patients receiving dialysis: a randomized controlled trial. JAMA. 1999;281(14):1275–1281. PMID: 10208142.
- Kicman AT. Pharmacology of anabolic steroids. British Journal of Pharmacology. 2008;154(3):502–521. PMCID: PMC2439524.
Disclaimer: This article is educational information from the Oxygen Anabolics team, not medical advice. Anabolic steroids are controlled substances in Canada and carry serious health and legal risks. Discuss any use with a qualified doctor, get bloodwork before and after, and seek prompt medical care for any warning symptoms.
