

Blog
When to Start PCT After Each Ester: A Timing Guide for Every Injectable

Post-cycle therapy (PCT) fails most often before it starts — not because the drugs are wrong, but because the timing is. Start a SERM while a long ester is still releasing hormone and the SERM fights an uphill battle: the hypothalamus still sees plenty of androgen, so LH and FSH stay suppressed. Wait too long, and you spend extra weeks in a low-testosterone trough for no benefit. The fix: do not set your PCT start date from the calendar. Set it from the ester.
The short version: short esters clear in days, so PCT can usually begin 2–3 days after the last injection; testosterone enanthate needs roughly 14 days; testosterone cypionate roughly 18 days and nandrolone decanoate roughly 21 days. Those windows are the commonly cited starting points in cycle practice — not prescriptions, and bloodwork always overrides them.
This guide is educational information from the Oxygen Anabolics team, not medical advice. If you are coming off a cycle, talk to a doctor and get bloodwork first.
Why PCT timing matters at all
On cycle, exogenous androgen tells the hypothalamus and pituitary to stop signalling the testes. LH and FSH fall and natural testosterone production drops. PCT drugs — most commonly the SERMs tamoxifen (Nolvadex) and clomiphene (Clomid) — block estrogen’s negative feedback at the hypothalamus, helping LH and FSH rise again. That only works once circulating androgen has fallen far enough for the feedback loop to respond; give a SERM at full androgen levels and you are pressing the accelerator with the handbrake still on. The gap itself is also a low-androgen window of fatigue, low libido and low mood, so a well-timed PCT shortens the worst of it without starting so early that the SERM is wasted. Our head-to-head guide, Nolvadex vs Clomid for PCT, covers which drug fits which situation; this guide covers when either should begin.
The half-life rule behind every window
An ester is a fatty-acid chain attached to the hormone. After injection, the hormone sits in an oil depot and is released slowly as enzymes clip the ester off. A longer chain means slower release and a longer half-life — the time for blood levels to fall by half. After one half-life about 50% remains; after two, about 25%; after four, about 6%. That decay is why PCT windows roughly correspond to three to five half-lives after the last injection.
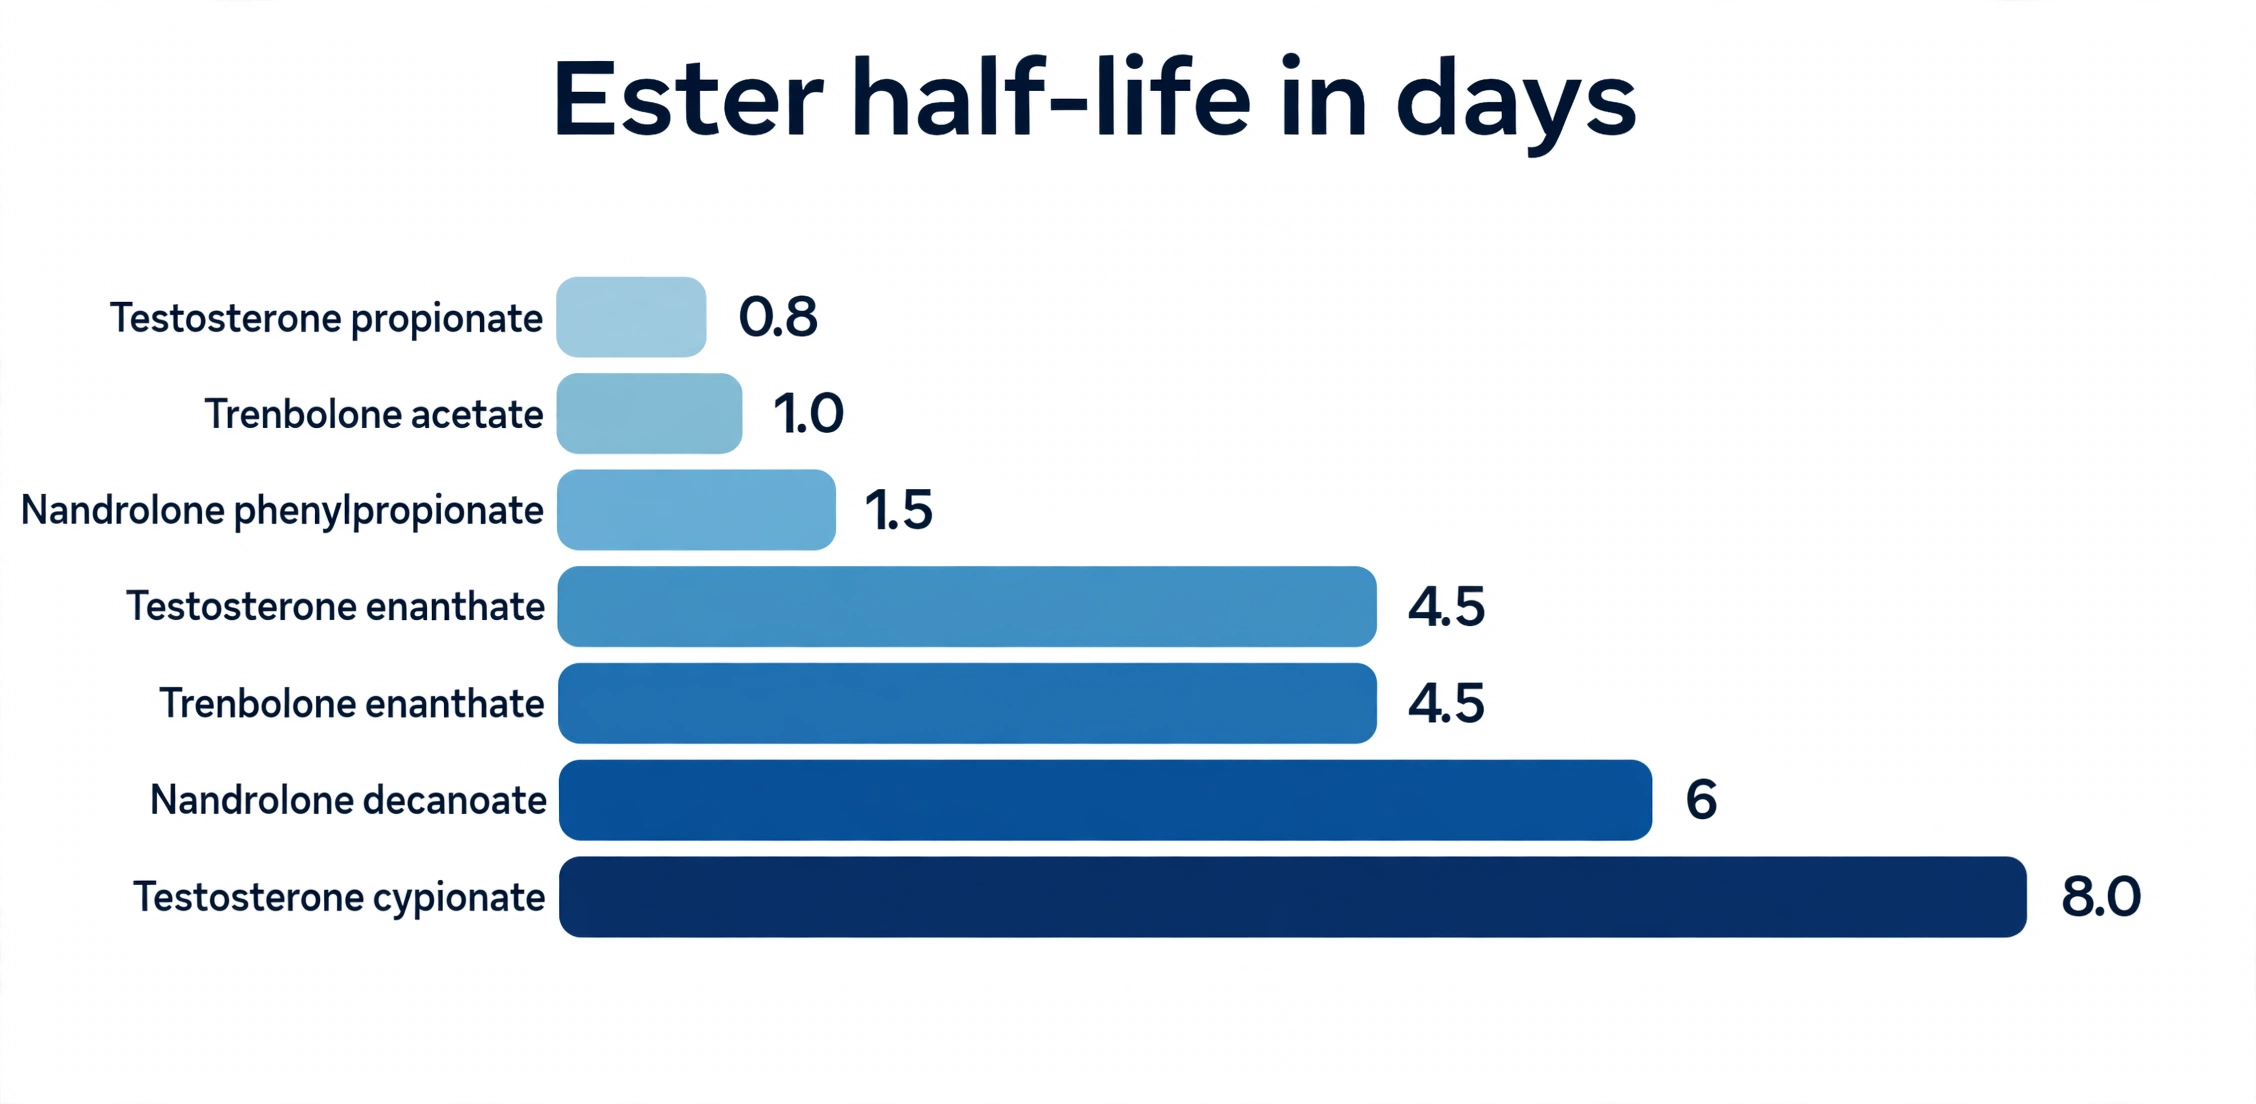
Three verified numbers anchor the chart. Testosterone enanthate has a terminal half-life of about 4.5 days; testosterone cypionate lasts longer, at roughly 8 days (an upper-end estimate — reviews report a range); nandrolone decanoate has a mean depot-release half-life of 6 days in healthy volunteers. Those figures explain why enanthate waits about two weeks, cypionate a little longer, and Deca longest. Half-lives vary with injection site, carrier oil, dose and metabolism, so treat the windows as starting points, not guarantees.
PCT timing chart: every major ester
Read the table left to right: the ester, its commonly cited half-life, the commonly cited window before PCT begins, and the reasoning. If you used a blend, use the longest ester in the blend (see below). If you used orals only, the wait is far shorter, because oral half-lives are measured in hours.
| Ester / compound | Half-life (days) | Commonly cited PCT start | Why this window |
|---|---|---|---|
| Testosterone propionate | 0.8 | 2–3 days after last injection | Short ester; largely cleared within a few days. |
| Trenbolone acetate | 1.0 | 2–3 days after last injection | Short ester; mirrors propionate timing. |
| Nandrolone phenylpropionate (NPP) | 1.5 | 5–7 days after last injection | Short nandrolone ester, slower than propionate. |
| Testosterone enanthate | 4.5 | About 14 days after last injection | Roughly three half-lives; the standard two-week wait. |
| Trenbolone enanthate | 4.5 | About 14 days after last injection | Same ester length as testosterone enanthate. |
| Nandrolone decanoate (Deca) | 6 | About 21 days after last injection | Longest common ester; depot-release half-life 6 days. |
| Testosterone cypionate | About 8 | About 18 days after last injection | Longest testosterone ester; wait longer than enanthate. |
| Oral steroids (e.g. Dianabol, Anavar, Winstrol) | Hours (about 5–10) | 1 day after last dose | No oil depot; fast clearance, but suppression still needs PCT. |
Caution: half-life definitions differ by source, so figures for one ester can vary by a day or two; cypionate ranges from about 5 to 8 days. The chart uses upper-end values because PCT timing should err slightly late.
Half-life at a glance
For the SERM side of the plan, the standard presentations discussed in our PCT guides are Nolvadex 20 mg tablets and Clomid 50 mg tablets, and the full range sits in the post-cycle therapy category. Which SERM, at what dose and for how long, is a medical decision — the chart tells you when the window opens, not what to take in it.
Three worked examples
1. A short-ester cycle (propionate or trenbolone acetate)
Your last injection is on a Monday. By Thursday, roughly three half-lives have passed and levels have fallen sharply, so PCT commonly begins around day 2–3. The gap is short, but the hormonal drop is sharper.
2. A testosterone enanthate cycle
Your last enanthate injection is on day 0. With a 4.5-day half-life, levels halve around day 4–5, halve again around day 9, and sit near one-eighth of peak around day 13–14, so the commonly cited PCT start is about day 14. Starting at day 7 would mean running a SERM against roughly a quarter of the peak dose still circulating. Our guide to testosterone enanthate vs cypionate explains why cypionate’s longer half-life pushes its wait a few days further.
3. A blend or a stacked cycle (including Sustanon)
For blends, the rule is simple: time PCT from the longest ester in the mix. A blend with a decanoate component, or any cycle including nandrolone decanoate, waits on the decanoate clock — about 21 days — even if the other compounds cleared weeks earlier.
Five timing mistakes that waste a PCT
Starting on a fixed date regardless of ester. “PCT starts two weeks after my last jab” is right for enanthate and wrong for almost everything else — far too late for propionate, too early for Deca. Anchor to the ester, not to a slogan.
Counting from the wrong last dose. In a stacked cycle, the “last injection” that matters is the last injection of the longest-acting compound. A late top-up of the long ester resets the clock; an oral finisher does not.
Using hCG as if it were PCT. Human chorionic gonadotropin stimulates the testes directly and can have a role before PCT in some medically supervised plans, but it also suppresses LH while used, so it is not a substitute for a SERM-based PCT.
Skipping bloodwork and judging by feel. Libido, energy and mood lag behind hormones and are confounded by training, sleep and stress. Only bloodwork shows whether LH, FSH and testosterone have actually recovered.
Running no PCT at all. Natural recovery does occur in many people over weeks to months, but the untreated trough is where muscle loss, depression and relapse into use cluster. See do you need PCT after a test cycle and the importance of post-cycle therapy after a steroid cycle, and discuss your case with a doctor.
Bloodwork: what to check, and when
Bloodwork is the only honest scoreboard for PCT timing. Ideally you have a pre-cycle baseline, so recovery is measured against your own normal. The panel a doctor will typically consider includes total and free testosterone, LH, FSH, estradiol, SHBG, prolactin, a complete blood count, and a lipid profile. A sensible rhythm, to agree with your doctor, is: baseline before the cycle, a check at the end of the gap before PCT starts, and a follow-up four to six weeks after PCT ends.
Two traps: a reading taken while a SERM is still active can look better than true recovery, because the SERM itself drives LH, so check after the SERM has cleared. And a single low reading during the gap is expected; what matters is the trend. Persistent problems months later need medical care, not another cycle. Harm-reduction basics: sterile technique, never share vials or needles, and urgent care for chest pain, breathlessness, leg swelling, severe mood change, or infection at an injection site.
The numbers, in one place
Three verified figures carry this guide: testosterone enanthate about 4.5 days, nandrolone decanoate 6 days (mean depot-release half-life), and testosterone cypionate roughly 8 days at the upper end of estimates. Four half-lives leave about 6% of a dose remaining, which is why PCT windows of three to five half-lives are the norm. Every number here also appears in the table and bar chart above.
Frequently asked questions
Can I start PCT early and just run it longer?
No. While androgen levels are still high, the feedback loop the SERM targets is still suppressed, so early weeks add side-effect exposure without the intended LH rise. Wait for the window instead.
What if I used both a short and a long ester?
Time PCT from the longest ester, always. A cycle ending with trenbolone acetate but containing nandrolone decanoate waits on the decanoate clock (about 21 days).
Do oral-only cycles need a PCT wait at all?
Yes, but a short one: orals clear within a day, so PCT commonly begins about one day after the last dose. Orals still suppress natural testosterone.
How do I know my PCT actually worked?
Bloodwork after the SERM has cleared — testosterone, LH and FSH back toward your pre-cycle baseline — plus symptom resolution. A single good reading during PCT is not proof, because the SERM itself raises LH.
Disclaimer
This article is educational information only, not medical advice. Steroids can cause serious harm, including cardiovascular disease, liver injury, infertility, mood disorders and dependence, and non-prescribed use is illegal in many jurisdictions, including Canada. Talk to a healthcare professional before any decision about stopping, starting or changing a drug, and seek urgent care for chest pain, breathlessness, severe mood change, or signs of infection. The Oxygen Anabolics team does not encourage non-prescribed steroid use.
References
- Kicman AT. Pharmacology of anabolic steroids. British Journal of Pharmacology. 2008;154(3):502–521. PMC2439524.
- Wijnand HP, Bosch AMG, Donker CW. Pharmacokinetic parameters of nandrolone (19-nortestosterone) after intramuscular administration of nandrolone decanoate (Deca-Durabolin) to healthy volunteers. Acta Endocrinologica Supplementum (Copenhagen). 1985;271:19–30.
- Pope HG Jr, Wood RI, Rogol A, Nyberg F, Bowers L, Bhasin S. Adverse health consequences of performance-enhancing drugs: an Endocrine Society scientific statement. Endocrine Reviews. 2014;35(3):341–375. PMID 24423981.
- Behre HM, Nieschlag E. Testosterone preparations for clinical use in males. In: Nieschlag E, Behre HM, eds. Testosterone: Action, Deficiency, Substitution. 3rd ed. Cambridge University Press; 2004.
