

Blog
Anadrol vs Dianabol: Which Oral Bulking Steroid Fits Your Goal?

If your goal is raw scale weight as fast as possible, Anadrol is the stronger of the two. If your goal is a fast strength jump with a fuller, pump-driven look and a reputation — rightly or not — for being slightly less brutal, Dianabol is the one lifters usually reach for first. That comes with a large qualification: neither is mild or safe, and no head-to-head trial in healthy athletes compares the two. Both are 17-alpha-alkylated orals, both strain the liver, suppress testosterone, raise blood pressure and worsen lipids. The choice is about which trade-offs you accept — and whether either is worth it.
This comparison separates what trials demonstrated from gym lore. The strongest direct evidence for Anadrol comes from a controlled trial in people with HIV-associated wasting, not bodybuilders; the Dianabol side rests on older pharmacology and class reviews. Read it as educational information, not medical advice: talk to a doctor first and get baseline bloodwork. Oxygen Anabolics publishes these comparisons so readers can weigh claims against evidence rather than marketing.
Anadrol at a Glance
Anadrol is oxymetholone, a DHT-derived drug developed for medical use, including anaemia from deficient red-cell production. It is a potent anabolic agent: weight gain in trials was substantial, but so was liver toxicity. Anadrol 25 mg tablets are the tablet strength listed in the store; dosing discussion below refers to trial doses, not an approved bodybuilding regimen — none exists.
What lifters report from Anadrol is rapid, heavy weight gain in the first weeks, much of it water, with large strength increases. Appetite often rises, but headaches, lethargy and appetite loss can follow as liver strain builds. Anadrol does not convert to oestrogen through aromatase in the usual way, yet users still report water retention and gynaecomastia-type symptoms; the mechanism is not fully settled, so oestrogen management on Anadrol is less predictable.
Dianabol at a Glance
Dianabol is methandrostenolone (methandienone), one of the oldest oral steroids, long associated with rapid strength and size gains at a cycle’s start. It aromatises to oestrogen, so water retention, fullness and oestrogen side effects are central to its profile. Dianabol 10 mg tablets are the tablet strength listed in the store; as with Anadrol, there is no approved performance dose.
What lifters report from Dianabol is a fast “on” feeling: pumps, fullness and strength gains within the first couple of weeks, often described as more usable strength than Anadrol’s blunt mass gain. The trade-off is the same family of problems — liver strain, blood pressure and lipid changes, suppression, acne and hair loss — plus oestrogen effects that are easier to anticipate but still need managing.
Head-to-Head Comparison
| Feature | Anadrol (oxymetholone) | Dianabol (methandrostenolone) |
|---|---|---|
| Compound class | 17-alpha-alkylated oral, DHT-derived | 17-alpha-alkylated oral, testosterone-derived |
| Reported half-life (approx.) | About 8–9 hours | About 4.5–6 hours |
| Typical reported use | Rapid mass gain, breaking a size plateau | Strength and fullness, cycle kick-start |
| Water retention | High; mechanism less predictable | High; driven by aromatisation to oestrogen |
| Oestrogen effects | Reported despite low aromatisation | Expected: gynaecomastia risk, bloating |
| Liver strain | High; trial liver toxicity was dose-related | High; 17-alpha-alkylated class effect |
| Approx. detection window | Up to about 8 weeks | Up to about 5–6 weeks |
| Best-known trial evidence | Hengge 2003, HIV wasting (see below) | No comparable modern efficacy trial |
Half-lives and detection windows are commonly reported approximate ranges, not guarantees. The table’s real message is simpler: on every risk axis that matters (liver, lipids, blood pressure, suppression), both sit in the same high-risk group; the differences are of degree, not kind. Our oral steroids category lists both alongside the other orals — choosing between them is choosing within one harsh class, not escaping it.

What the Numbers Actually Show
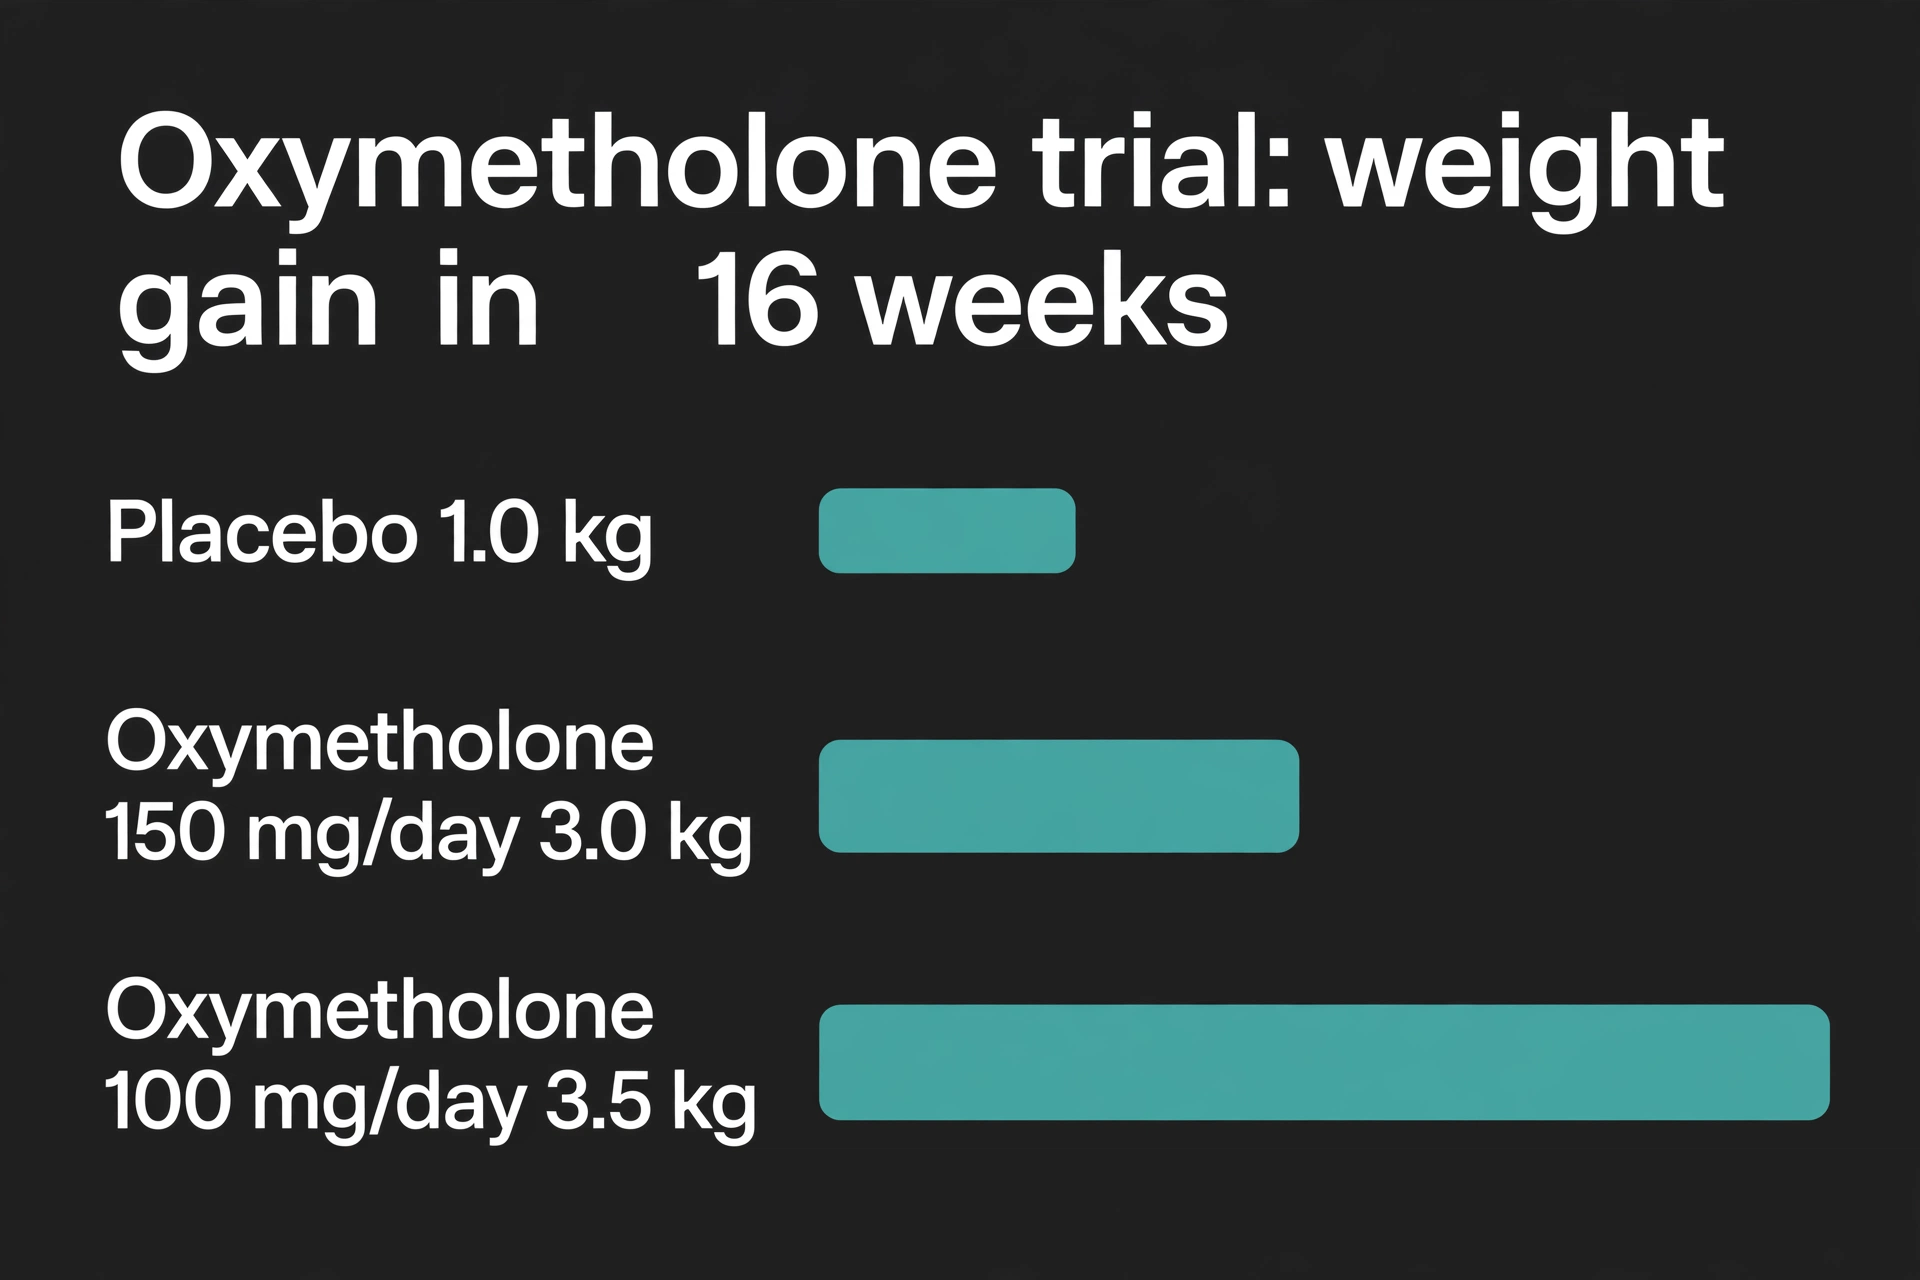
The cleanest numbers here come from Hengge and colleagues: a double-blind, placebo-controlled phase III trial of oxymetholone in 89 HIV-positive men and women with wasting. Over 16 weeks, the 50 mg twice-daily group (100 mg per day) gained 3.5 kg, the 50 mg three-times-daily group (150 mg per day) gained 3.0 kg, and placebo gained 1.0 kg. Body cell mass rose 3.8 kg and 2.1 kg respectively. Strikingly, the lower dose matched the higher dose for weight gain — with less liver damage.
| Hengge 2003 group (16 weeks) | Mean weight gain | Body cell mass gain | ALT rise over 5x baseline |
|---|---|---|---|
| Placebo | 1.0 kg | — | 0% |
| Oxymetholone 150 mg/day (TID) | 3.0 kg | 2.1 kg | 35% |
| Oxymetholone 100 mg/day (BID) | 3.5 kg | 3.8 kg | 27% |
Mean weight gain over 16 weeks, Hengge et al. 2003. Bars scaled to the largest value (3.5 kg = 100%).
The liver figures cut against “more is better” logic: 27% of the 100 mg-per-day group and 35% of the 150 mg-per-day group had an ALT rise to more than five times baseline, against none on placebo. For the class as a whole, a 2025 systematic review and meta-analysis found pooled increases of 12.43 mmHg in systolic blood pressure, 9.12 mg/dL in LDL cholesterol and 12.16 U/L in ALT, with testosterone falling 141.57 ng/dL after use. An older athlete review found short-term strength gains of about 5–20% and bodyweight gains of 2–5 kg — a reminder that dramatic gym stories are not what controlled studies show, and much rapid scale weight on either oral is water that leaves when the drug stops.
Side Effects, Side by Side
Liver. Both carry the 17-alpha-alkylated structure that lets them survive first-pass metabolism — and that is exactly what stresses the liver. Cholestatic jaundice is the most commonly reported hepatic problem, with peliosis hepatis and liver tumours reported rarely with long-term use. In Hengge, liver toxicity was the most important adverse event, rose with dose, and appeared within a 16-week medical trial. Baseline and follow-up liver tests (ALT, AST, bilirubin, alkaline phosphatase) are a minimum harm-reduction step; jaundice, dark urine, pale stools, itching or right-upper-abdominal pain mean stop and seek care promptly.
Oestrogen, water and blood pressure. Dianabol’s oestrogen effects are the more predictable: aromatisation brings bloating, water retention and gynaecomastia risk, and the water pushes blood pressure up. Anadrol’s retention is less predictable and harder to manage with a standard aromatase inhibitor. Blood pressure should be monitored either way, and anyone with hypertension, heart or kidney disease should treat both as off-limits without specialist advice.
Lipids, suppression and appearance. Oral 17-alpha-alkylated steroids are particularly hard on HDL cholesterol, and the 2025 meta-analysis figures above describe the class, not an exception. Both suppress natural testosterone, so low mood, low libido and fatigue after stopping are common, and fertility can be affected while suppressed. Acne, oily skin and accelerated hair loss in susceptible men apply to both; in women, virilisation (voice deepening, hair growth, menstrual disruption, some irreversible) makes the risk profile distinctly worse.
Cycle Structure, Stacking and PCT
Community reports usually keep either oral to about four to six weeks, often at the start of a longer injectable cycle, because liver and lipid strain accumulate with duration. Stacking Anadrol and Dianabol together combines two liver-toxic orals with overlapping side effects and no evidence of added benefit; this guide does not recommend it. A testosterone base is the usual community pattern for either oral, because an oral alone suppresses testosterone without replacing it — but that adds its own oestrogen, blood and fertility considerations.
Post-cycle therapy is not optional after either drug: once the oral stops, natural testosterone is suppressed and oestrogen balance is in flux. Timing depends on the rest of the cycle, especially any long-ester injectable. Related guides: Dianabol benefits, Anadrol uses, estrogen management on cycle and Nolvadex vs Clomid for PCT. If PCT drugs are unavailable or bloodwork cannot be done, that is a reason not to start.
Which One Fits Which Goal?
Choose the Anadrol profile if the priority is maximum scale weight in a short window and you accept the highest liver-strain trade-off here — remembering Hengge: the lower dose matched the higher dose for weight gain with less liver toxicity. Choose the Dianabol profile if the priority is strength and a fuller look with oestrogen effects that are at least predictable, accepting that much early gain is water. Choose neither if you have liver, heart, blood-pressure or prostate problems, you are a tested athlete, you are a woman, or you cannot get bloodwork and PCT in place.
Harm-Reduction Checklist
Get baseline bloodwork (full blood count, liver panel, lipids, testosterone, oestradiol, kidney function and blood pressure), and repeat it during and after use. Avoid alcohol and paracetamol-heavy painkillers while on either oral, keep cycles short, never stack two 17-alpha-alkylated orals, and do not use either drug if pregnant, trying to conceive, or managing liver or heart disease. See a doctor promptly for jaundice, severe abdominal pain, chest pain, breathlessness, marked swelling, severe mood change or thoughts of self-harm.
Frequently Asked Questions
Is Anadrol stronger than Dianabol?
For raw scale weight, yes — oxymetholone is generally regarded as the more potent mass drug, and Hengge showed several kilograms of gain in a medical population. For usable strength and a fuller look, many lifters prefer Dianabol. “Stronger” also means harsher on the liver.
Can you take Anadrol and Dianabol together?
It is discussed online, but it stacks two liver-toxic orals with overlapping risks and no trial evidence of added benefit. This guide does not recommend it.
How much weight will I keep after stopping?
Less than the scale shows during the cycle. Much early oral gain is water; controlled data show modest tissue gains (2–5 kg in athlete reviews, 3.0–3.5 kg in the oxymetholone trial). What remains depends on training, nutrition and testosterone recovery after PCT.
Do I need PCT after an Anadrol or Dianabol cycle?
Yes. Both suppress natural testosterone, and stopping without a recovery plan risks prolonged low testosterone, fatigue and muscle loss. Plan PCT before the cycle starts, not after it ends.
References
- Hengge UR, Stocks K, Wiehler H, et al. Double-blind, randomized, placebo-controlled phase III trial of oxymetholone for the treatment of HIV wasting. AIDS. 2003;17(5):699–710. PMID 12646793.
- Liu M, Yu Y. Adverse effects of anabolic androgenic steroid abuse in athletes and physically active individuals: a systematic review and meta-analysis. Substance Use & Misuse. 2025;60(6):873–887. PMID 39945139.
- Hartgens F, Kuipers H. Effects of androgenic-anabolic steroids in athletes. Sports Medicine. 2004;34(8):513–534. PMID 15248788.
- Pope HG Jr, Wood RI, Rogol A, Nyberg F, Bowers L, Bhasin S. Adverse health consequences of performance-enhancing drugs: an Endocrine Society scientific statement. Endocrine Reviews. 2014;35(3):341–375.
Disclaimer: This article is educational information only and is not medical advice. Anabolic steroids can cause serious liver, cardiovascular, hormonal and psychological harm, and non-medical use may be illegal in your jurisdiction. Talk to a qualified healthcare professional before making any decision about these compounds, and seek urgent medical care for any concerning symptom.
